
Symptoms
Low Back Pain: Trigger Points and Muscles Involved
Region: Torso
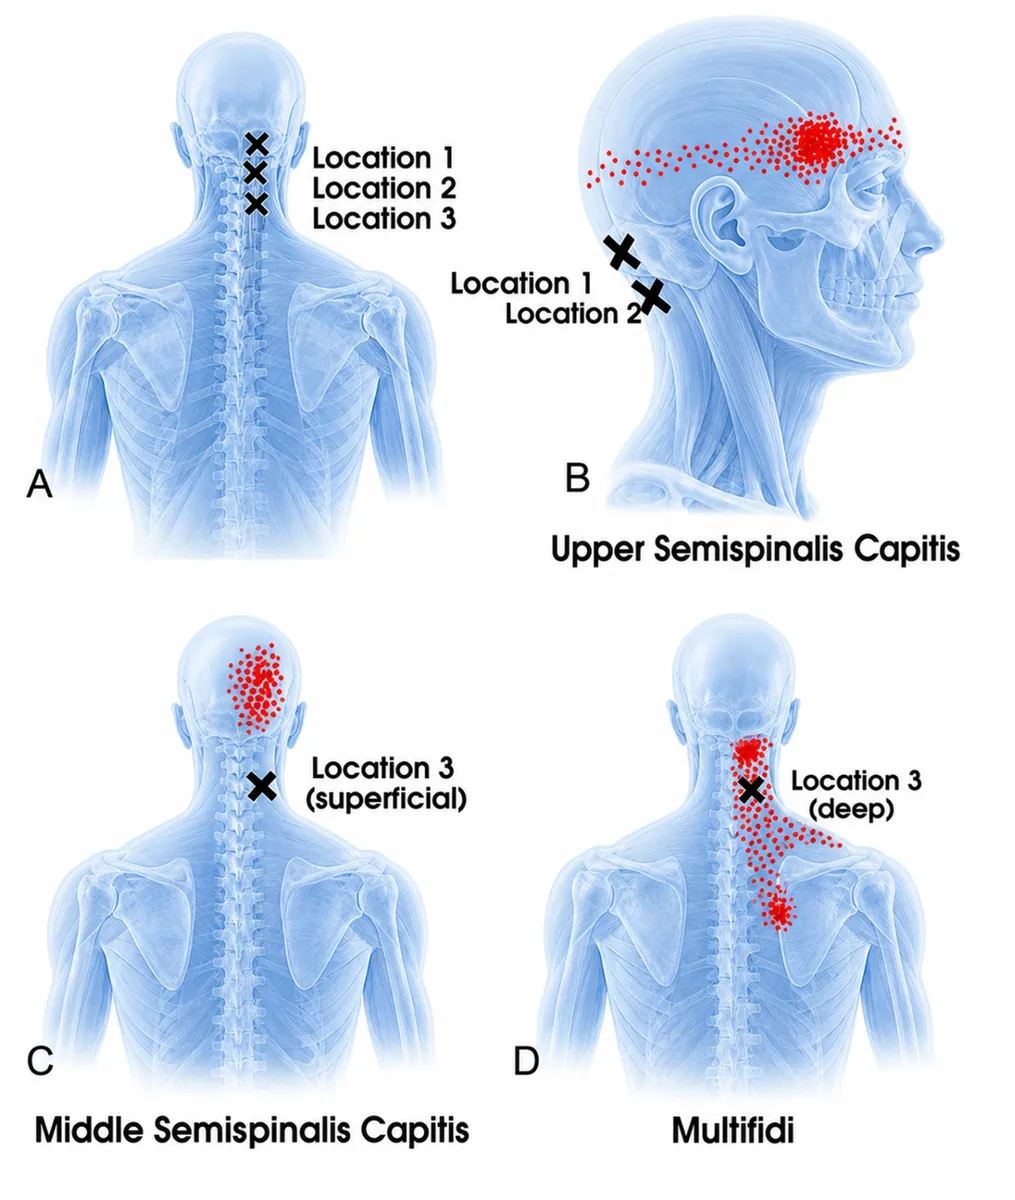
Low Back Pain: trigger points and referred pain. Primary muscles in this reference: Quadratus Lumborum, Longissimus Thoracis, Iliocostalis Lumborum, Iliocostalis Thoracis, Multifidi, Rectus Abdominis.
Overview
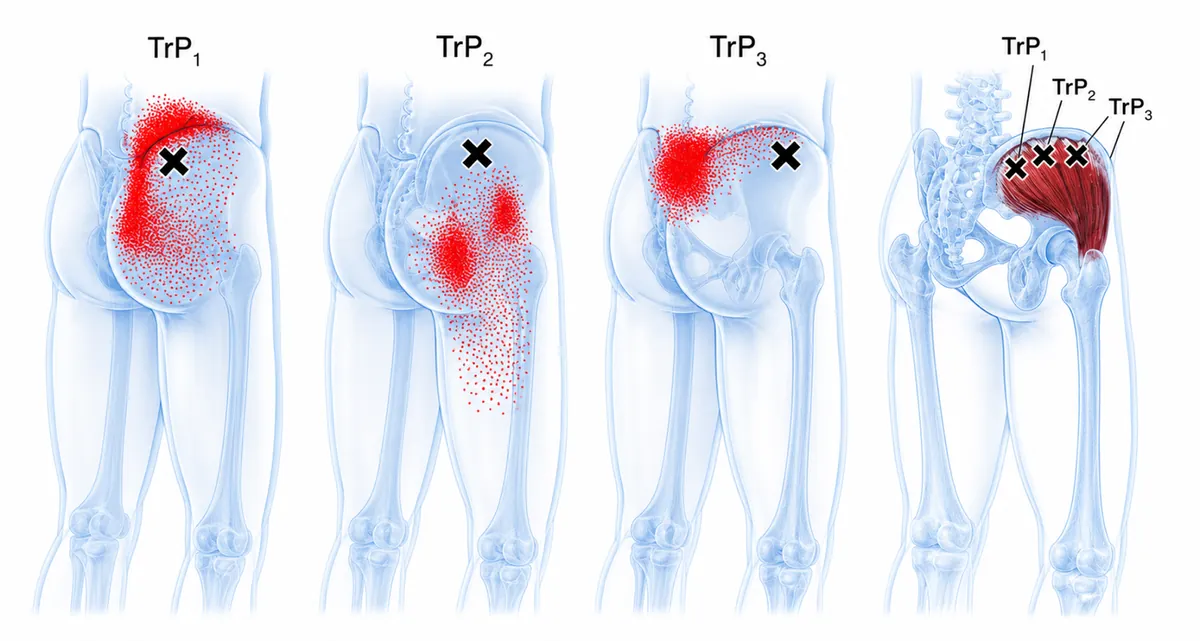
The primary muscles listed for Low Back Pain are Quadratus Lumborum, Longissimus Thoracis, Iliocostalis Lumborum, Iliocostalis Thoracis, Multifidi, Rectus Abdominis. Trigger points can produce referred pain: discomfort is felt away from the tender muscle. “Muscle knots” is an everyday description, whereas myofascial pain is the clinical term used in the linked references. This is a reference association, not proof that a muscle causes this symptom. A pain map cannot rule out joint, nerve or internal-organ conditions. Match the exact location and circumstances, rather than treating every tender spot as the source.
The primary associations for Low Back Pain are Quadratus Lumborum, Longissimus Thoracis, Iliocostalis Lumborum, Iliocostalis Thoracis, Multifidi, Rectus Abdominis. Primary, secondary and tertiary describe the reference's ordering, not a diagnosis or a measured probability. The following extracts describe each muscle's complete referral pattern; not every area mentioned is necessarily part of your symptom.
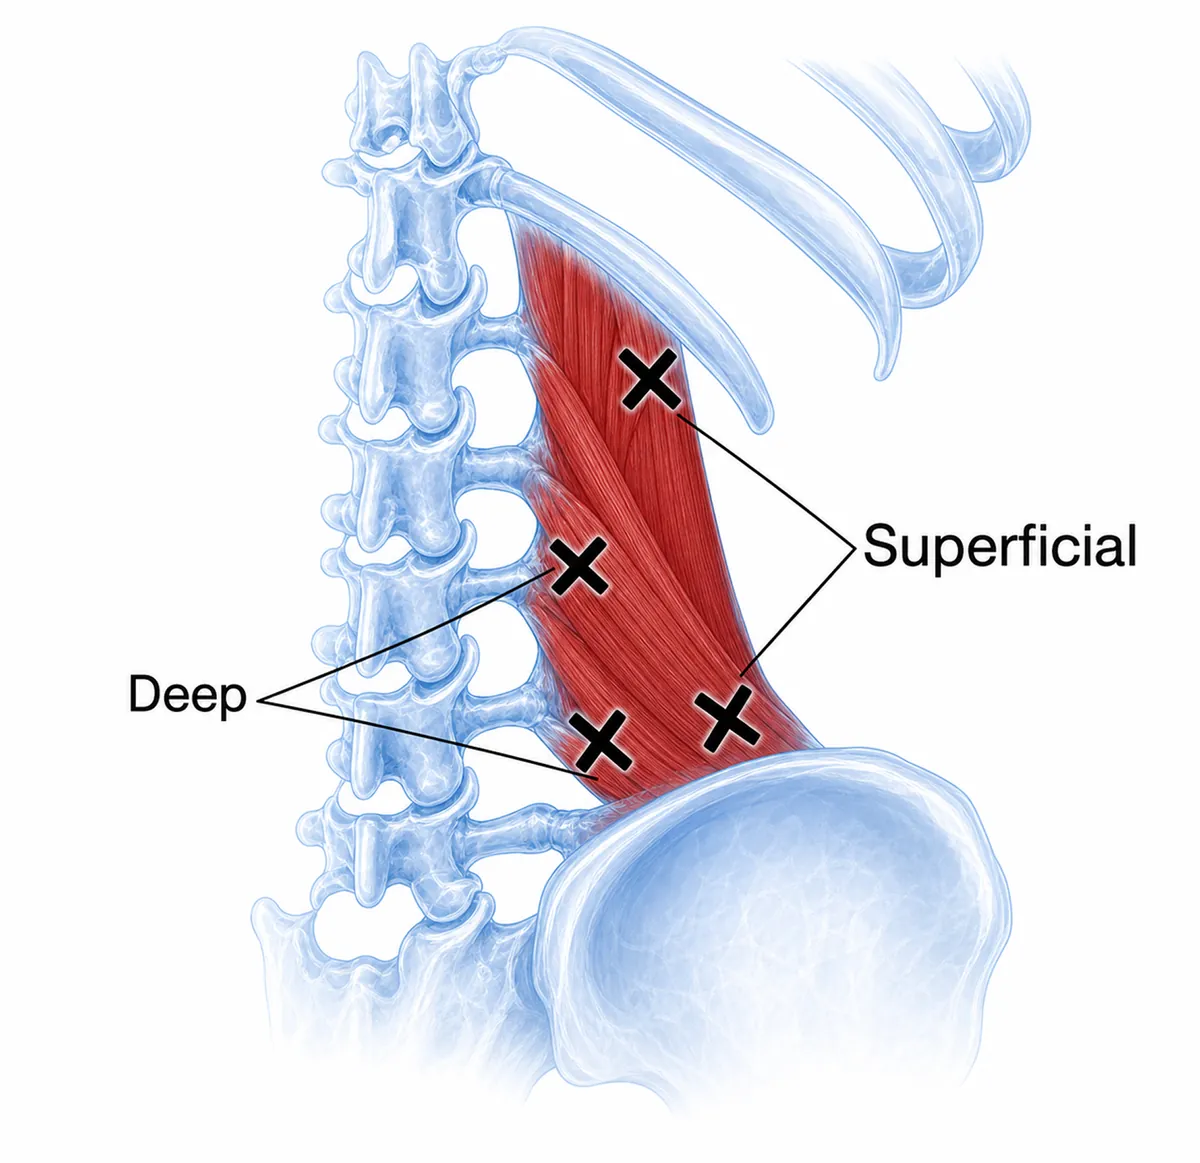
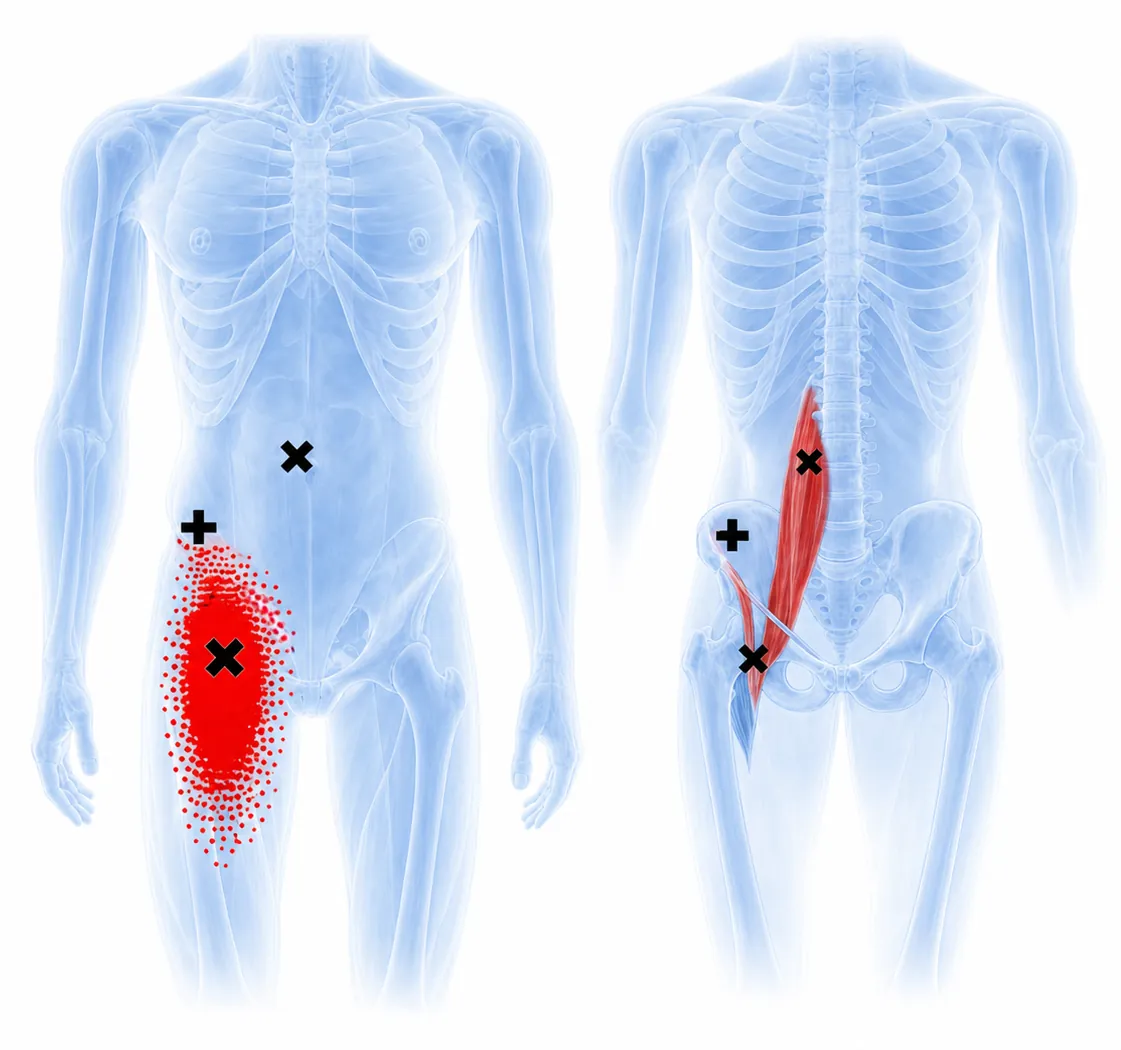
Quadratus Lumborum — Iliac crest, sacroiliac joint area, greater trochanter, sometimes lower abdominal pain. Often described as a deep, dull lumbar ache.
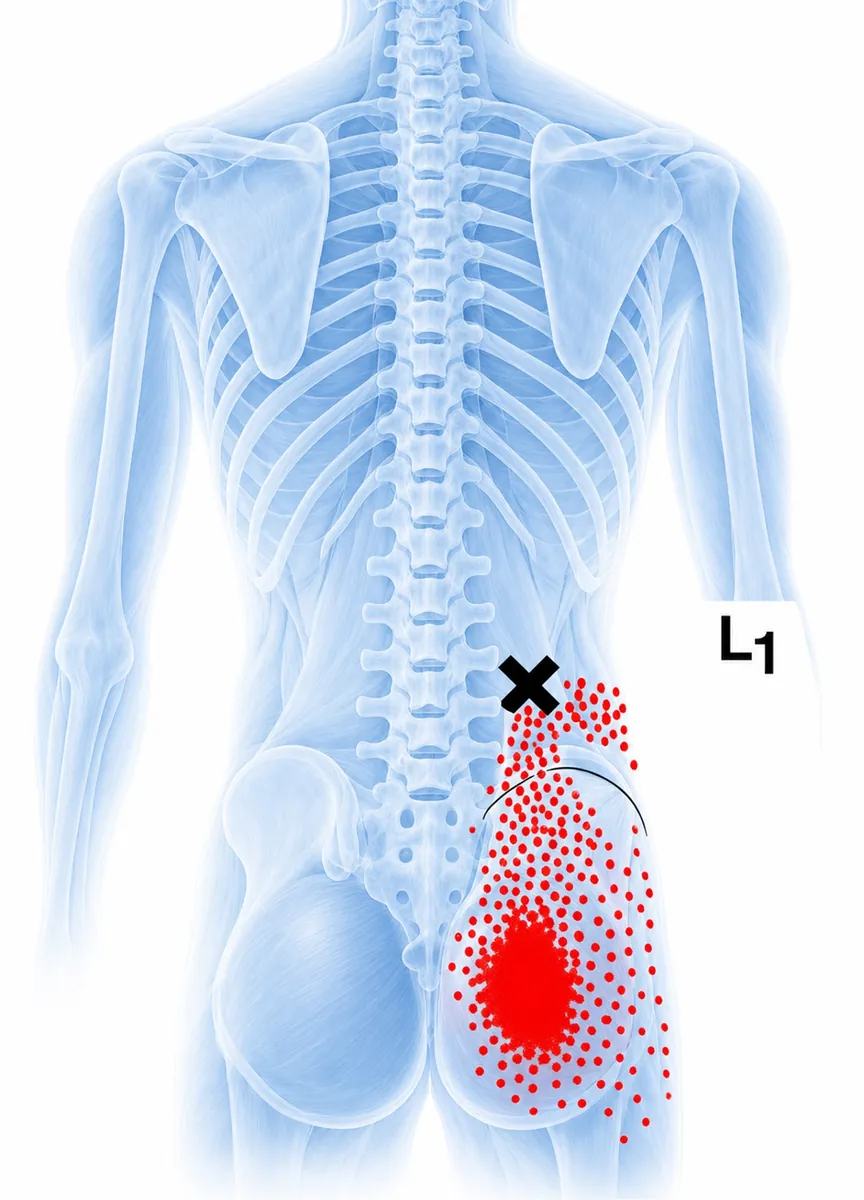
Longissimus Thoracis — Buttock and lateral lower back pain, mimicking 'sciatica' but staying above the knee.
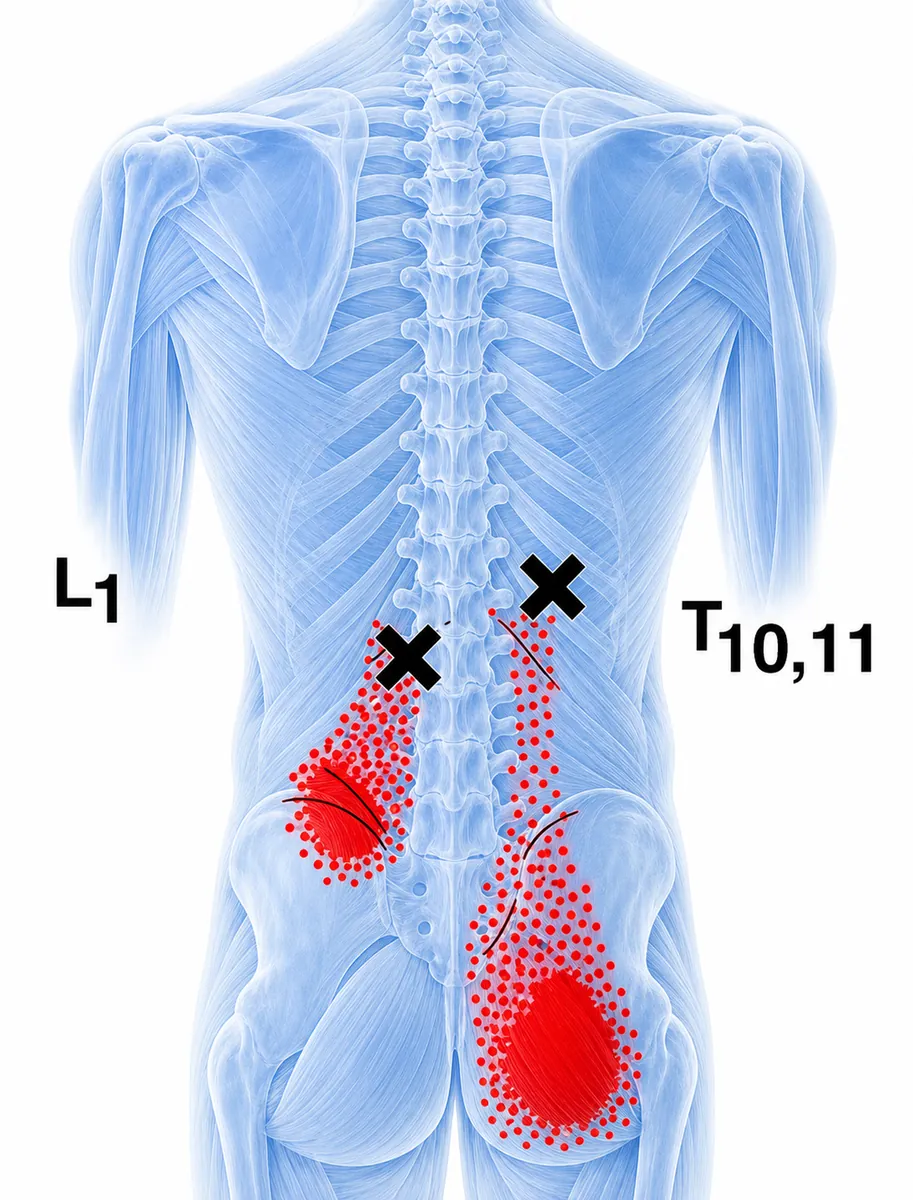
Iliocostalis Lumborum — Lower back pain along the iliac crest, sometimes wrapping to the lower abdomen.
Iliocostalis Thoracis — Upward referral toward the upper back and shoulder blade, downward referral toward the lumbar region, and wrap-around pain over the lateral chest wall.
Multifidi — Local segmental pain, often felt as a 'spot' the patient can point to.
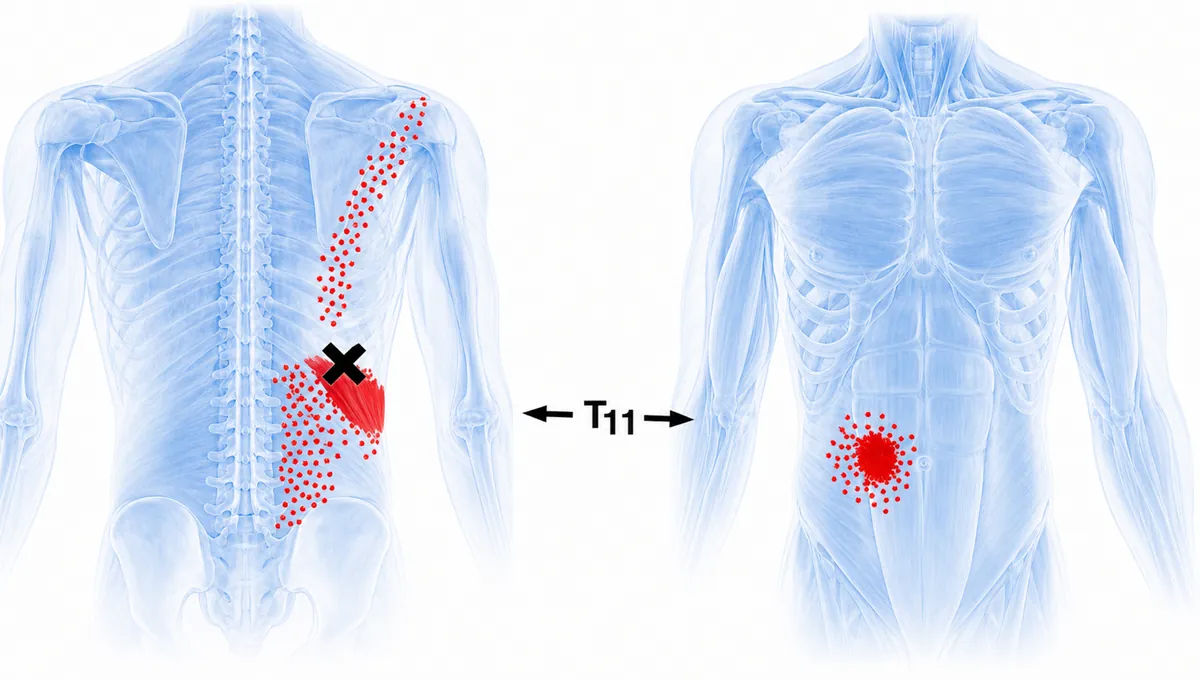
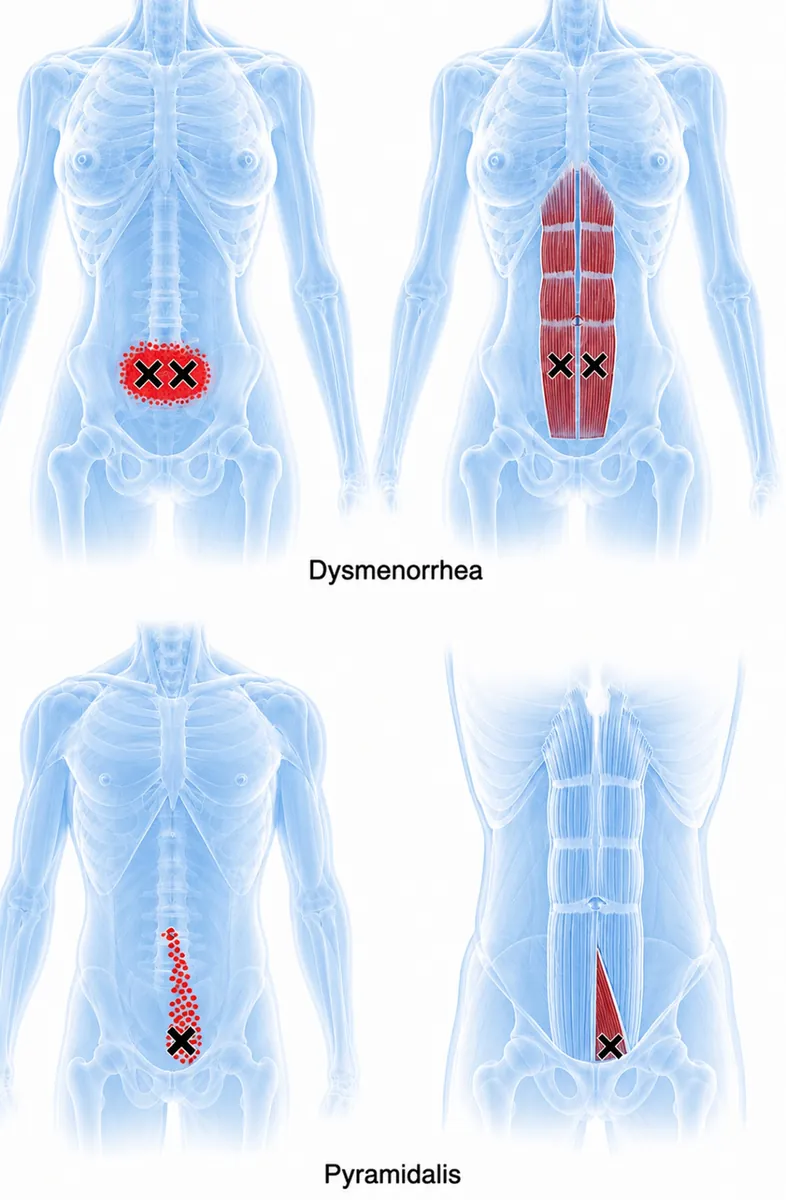
Rectus Abdominis — Mid-back and lower-back pain, urinary urgency-like sensations, abdominal cramps.
Record where Low Back Pain occurs, which position or activity changes it, and whether it is accompanied by numbness, weakness or another symptom. Compare those observations with the linked muscle maps. A clinician can assess whether palpation reproduces the familiar complaint; tenderness alone does not establish the cause. Do not press deeply into the throat, abdomen or other sensitive areas to test a theory.
For Low Back Pain, begin with assessment of the symptom rather than assuming that release is needed. Where a muscular contribution has been assessed, the linked pages for Quadratus Lumborum, Longissimus Thoracis, Iliocostalis Lumborum, Iliocostalis Thoracis, Multifidi, Rectus Abdominis describe their existing self-care options, loading factors and precautions. Read those precautions before trying an exercise. Dry needling and injections are clinician-only procedures. Do not use a referral map to delay care or to stop an established treatment.
Quadratus Lumborum — Leg length discrepancy, asymmetric loading, sustained sitting in a twisted position, lifting with rotation. Side-lying with the upper arm overhead to open the flank. Palpate between the 12th rib and the iliac crest, lateral to the paraspinals. Side-bend stretches over a foam roller, address pelvic asymmetry, diaphragmatic breathing. Clinically: needling, lateral decubitus manual release.
Longissimus Thoracis — Prolonged seated posture, repetitive bending. Palpate the muscle belly along its accessible course. Reproduction of the patient's familiar pain on palpation supports involvement. Hip hinge retraining, mobility. Clinically: needling.
Seek medical assessment for Low Back Pain when it is new, persistent, worsening or unexplained. Muscle associations are educational information, not a way to exclude other causes. The existing warning signs for this entry are: Saddle anesthesia, bilateral leg weakness, bladder/bowel changes, unexplained weight loss, history of cancer, fever, IV drug use — urgent referral.
For an appointment about Low Back Pain, bring a short record of the symptom rather than only the name of a suspected muscle. Note the activity before it started, whether the location has changed and what has already been tried. These observations help a professional compare the muscular associations with alternative explanations without relying on the atlas alone.
Primary Symptoms
Secondary Symptoms
Related articles
- Your MRI is not a diagnosis: what scans show in people without pain
- Self-treating a trigger point: pressure, heat and movement
- Referred pain: why the spot that hurts is rarely the spot that needs treatment
- The piriformis: the muscle that imitates sciatica from deep in the buttock
- Do stretching and exercise actually change a trigger point? What the trials show
- Low back pain that flares when you stand: a step-by-step quadratus lumborum treatment plan
FAQ
- Which muscles are listed for Low Back Pain?
- Quadratus Lumborum, Longissimus Thoracis, Iliocostalis Lumborum, Iliocostalis Thoracis, Multifidi, Rectus Abdominis. This is a reference association, not proof that a muscle causes this symptom. A pain map cannot rule out joint, nerve or internal-organ conditions. Match the exact location and circumstances, rather than treating every tender spot as the source.
- How can I check the pattern of Low Back Pain?
- Record where Low Back Pain occurs, which position or activity changes it, and whether it is accompanied by numbness, weakness or another symptom. Compare those observations with the linked muscle maps. A clinician can assess whether palpation reproduces the familiar complaint; tenderness alone does not establish the cause. Do not press deeply into the throat, abdomen or other sensitive areas to test a theory.
- Does Low Back Pain prove I have trigger points?
- This is a reference association, not proof that a muscle causes this symptom. A pain map cannot rule out joint, nerve or internal-organ conditions. Match the exact location and circumstances, rather than treating every tender spot as the source.
References
- • Travell & Simons, Vol. 2
- • Travell & Simons — Myofascial Pain and Dysfunction
- • triggerpoints.net — reference
Medically reviewed by: Marco Aruffo — physiotherapist since 2006, specialised in myofascial pain · Last reviewed:
